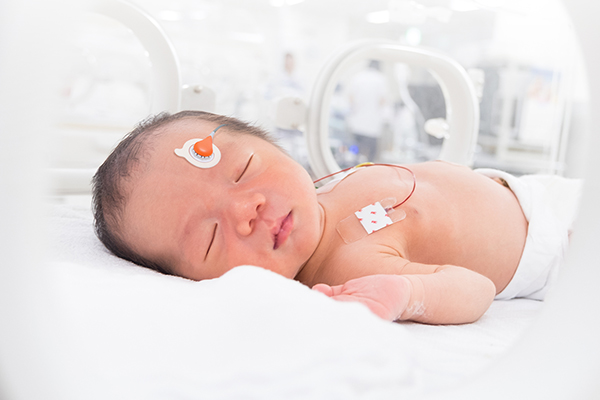
In the NICU, monitoring tools provide insight into an infant’s physiologic status, supporting clinical decision-making and helping teams assess response to therapy. Among the many parameters monitored, carbon dioxide (CO2) is particularly important, serving as a key indicator of how effectively an infant is ventilating. Equally important is selecting the right monitoring method, as this enables care teams to fully leverage CO2 data to guide precise and effective respiratory management.
By understanding the value of CO2 monitoring and choosing the most appropriate approach, NICU teams can detect changes early, adjust interventions as needed, and deliver individualized care.
The importance of effective CO2 monitoring
Data reveals that up to 46.5% of NICU admissions involve a respiratory component,¹ with many infants requiring noninvasive or invasive mechanical ventilation due to immature respiratory systems. During ventilation, the goal is to ensure adequate gas exchange (oxygenation and CO2 removal), while also minimizing ventilator induced lung injury (VILI). Because these infants are extremely fragile, maintaining that delicate balance is both challenging and critical for achieving the best possible outcomes.
To optimize ventilation, it is essential to monitor key gas exchange targets closely. CO2 is a direct reflection of how well ventilation matches metabolic demand, making it one of the most important parameters guiding ventilator management. Continuous CO2 monitoring not only shows whether settings are supporting effective gas exchange and helps clinicians avoid the risks of too-high or too-low CO2, but it also signals when support may be too strong — preventing potential lung overdistention and injury.
Methods of CO2 Monitoring in the NICU
CO2 monitoring can play an important role in guiding effective respiratory care in the NICU, but the method you choose matters. Each monitoring method offers different strengths and limitations, and understanding these can help care teams choose the approach that best supports their patients.
Arterial Blood Gas (ABG)
Arterial blood gas tests provide a direct measurement of PaCO2 using a blood sample, usually drawn from the radial or brachial artery.
The pros:
- Considered the gold standard for accuracy
- Provides multiple parameters in a single measurement (pH, CO2, O2, HCO2, electrolytes)
- Direct assessment of arterial blood gas values
The limitations:
- Invasive and carries the risk of infection
- Causes pain and stress for neonates, which has been shown to negatively affect short- and long-term outcomes
- Adds to overall blood loss, a meaningful risk for preterm babies with limited blood volume
- Only provides a point-in-time measurement, which can leave CO2 fluctuations to go undetected
In summary…
Arterial blood sampling is, and will continue to be, a vital tool in neonatal care, providing accurate, direct measurements of key parameters. However, inherent limitations, including pain, blood loss, and infection risk, underscore the need to consider supplemental strategies. The absence of continuous data is also a concern in the NICU, where even small changes can significantly impact fragile patients, emphasizing the value of methods that instead provide continuous, real-time insights.
The tCOM+ for the NICU
Transcutaneous CO2 monitoring can support NICU teams in guiding gentle, neuroprotective ventilation and reducing pain through fewer blood draws, overcoming many of the limitations associated with both ABGs and end-tidal monitoring.
The tCOM+ provides accurate, reliable tcPCO2 measurement, purpose-built for the needs of the NICU.

References: